Diagnosing Canine Hip Dysplasia
Wendy Baltzer, DVM, PhD, DACVS, DACVSMR, DECVS, CCRP, University of Minnesota
Surgical management, pharmacologic agents, nutrition, exercise, rehabilitation, stem cell therapy, and other treatment options are available in Treating & Preventing Canine Hip Dysplasia.
Overview
Canine hip dysplasia is a developmental orthopedic disease of the coxofemoral joint, in which joint laxity and incongruency may result in trauma to the articular cartilage and subchondral bone of the joint and development of osteoarthritis (OA). Not all puppies with hip dysplasia and clinical signs of hip joint laxity develop OA and lameness as adults.1-3
Epidemiology
Incidence/Prevalence
Hip dysplasia occurs in 15.6% of dogs in the United States and Canada; female dogs have an odds ratio of 1.05 for developing this disorder4; however, its true incidence is unknown because different reporting methods of breed testing and prevalence have been used and may have resulted in overrepresentation of some breeds.1,5-8
Breeds with the highest historical incidence are Newfoundlands, Saint Bernards, Old English sheepdogs, Rottweilers, German shepherd dogs, Samoyeds, golden retrievers, Alaskan malamutes, and Labrador retrievers.9
Signalment
Breed Predisposition
Breeds with longer body length-to-height ratios may have increased incidence.10
Breeds with a high body-to-mass ratio (kg/m2 body surface area), which is similar to body mass index in humans, may have an increased incidence.11
Age
In predisposed breeds, hip joints are grossly normal at birth, but disease develops in the first few months of life.12-14
At 2 to 4 months of age, alterations in extracellular matrix structure, myogenesis, and OA development of the hip are present. Puppies that develop OA may have increased incidence of OA in other joints as they age.7,15
Risk factors for hip dysplasia in puppies from predisposed breeds include:
Increased birth weight16
Large litter17
Born in the southern United States18
Born in winter or spring18
Neutered prior to 5.5 months of age (increased risk for euthanasia due to hip dysplasia)4
Diagnosis and medical or surgical treatment of hip joint laxity and pain as early as 2 to 4 months of age may improve long-term outcomes.19-21
Sex
Neutered male dogs are 33% more likely to develop hip dysplasia than intact males and females.9
The likelihood of female dogs developing hip dysplasia is slightly increased (5%) compared with males but can vary widely by breed (eg, 3.36 times more frequent in female Polish Tatra sheepdogs vs 1.63 times more frequent in male Afghan hounds).22
Genetic Implications
Although the exact pathophysiology is unknown, hip dysplasia is a polygenic inherited disorder with a complex mode of inheritance.
OA progression and severity of clinical signs depend on the interaction of many factors, including the presence of inherited OA genetics, genetic susceptibility, epigenetics, and exposure to environmental stressors.1
The heritability ratio of hip joint laxity, which may or may not lead to development of hip dysplasia, varies widely but has been estimated to be between 0.2 and 0.85, whereas the heritability ratio of hip dysplasia with OA of the hip has been reported as 0.43. These estimates are markedly determined by breed.3,11,23-28
Breeding programs that exclude dogs with hip joint laxity are more likely to reduce incidence of hip dysplasia than programs that only exclude dogs with radiographic evidence of coxofemoral joint OA.3,11
OA often results from prolonged hip joint laxity, joint subluxation, and articular cartilage damage. Many puppies develop hip joint laxity with or without radiographic evidence of OA, but some do not show signs of pain or lameness and have slower progression of joint OA on radiographs over time.3,28-31
German shepherd dogs without the gene encoding for a bone morphogenic protein inhibitor have reduced incidence of hip dysplasia, indicating protective and detrimental genetic factors can be involved, at least in some cases.15
Causes & Risk Factors
Hip dysplasia is a multifactorial disease with genetic and environmental factors related to expression in individual dogs. Rate of OA progression from onset in dogs with hip dysplasia is variable; however, faster progression may occur in spayed dogs and in dogs that develop OA while the growth plates are still open (ie, younger dogs).12,23,31-33
No commercial test is available to determine which dogs with the genotype will develop significant hip dysplasia later in life. Lumbosacral transitional vertebrae are associated with a higher occurrence of hip dysplasia in some breeds.34
Alterations of serum biomarkers (eg, hyaluronic acid, matrix metalloproteinase 9, procollagen type II C-terminal propeptide) and/or urine biomarkers (eg, C-telopeptide fragments of collagen type I and II) may provide evidence of clinical hip dysplasia in dogs and increase early detection; however, further validation is required.35-37
Environmental Factors
Environmental factors play a role and can be controlled by the pet owner and clinician to reduce the incidence and severity of the disease.3,18,38
Exercise and housing on slippery surfaces may increase severity of hip dysplasia from birth to 3 months of age.3
Puppies housed on fleece rather than newspaper during the first 3 weeks of life have reduced risk (from 1.94% to 0% in a study).19
Puppies born in spring or summer and those provided off-leash exercise on grass (soft ground) have reduced risk for development of hip dysplasia at 12 months of age.38
Nutritional Factors
Calcium supplementation increases risk in predisposed puppies.39,40
Low-anion gap diet reduces incidence of hip dysplasia in puppies.41
In a study, a fish-based diet high in omega-3 fatty acids was shown to reduce the severity of OA but not the incidence of hip dysplasia compared with control diets fed to hip-dysplasia–predisposed puppies 3 to 12 months of age.42
In another study, predisposed Labrador retriever puppies fed 25% less than ad libitum quantities developed hip joint OA 50% less frequently than littermates fed ad libitum.41,43
Limiting food intake (and body weight) over a dog’s lifespan can slow progression of radiographic signs of OA.41,43-46
Dogs fed ad libitum developed radiographic signs of hip OA at 6 years of age versus 12 years of age in restricted-fed dogs.43
Overweight dogs with hip OA demonstrated decreased lameness following weight reduction.47-49
Pregnancy
Increased birth weight and the number of puppies in a litter increase risk for hip dysplasia.4
Specific to Labrador Retrievers
Obesity, a high-fat diet, and exercise involving running after balls and sticks or other objects that stimulate sharp turns may increase risk for hip dysplasia development.26,49-51
Pathophysiology
Primary joint laxity can occur as a result of abnormal collagen turnover or fiber development in the joint capsule and ligament of the femoral head and result in joint subluxation.23 Abnormal endochondral ossification of the acetabulum can result in joint incongruency, joint effusion, and secondary subluxation and laxity.2 Synovitis, perifoveal cartilage damage, and joint effusion that occurs during growth (eg, 3-8 months of age) can result in OA at maturity.
Many dogs can develop hip joint laxity and show radiographic evidence of OA but may not exhibit signs of pain or lameness. Puppies with early signs of hip joint laxity may not develop hip OA as adults.29
Clinical Presentation
Dogs <1 year of age may exhibit lameness, stiffness in the pelvic limbs, and/or a bunny-hopping gait.
Adult dogs may exhibit OA-related lameness, difficulty climbing stairs and jumping, and stiffness when standing after resting.3
Physical examination may reveal:
Crepitus and pain when the hip is extended or abducted
Pelvic limb muscle atrophy
Decreased range of motion in the joint
Lameness in one or both pelvic limbs
Pain index
Affected dogs may have acute episodes of joint pain resulting in non–weight-bearing lameness, chronic pain, and lameness associated with OA.
Differential Diagnoses
Hip dysplasia should be suspected in immature dogs exhibiting pain on manipulation of hips.
Differential diagnoses include:
Septic coxofemoral joint (Figure 1)
Fracture of the pelvis or femoral head/neck, including capital femoral physis
Neoplasia of the femur/pelvis and surrounding tissue
Iliopsoas myopathy/tendonitis
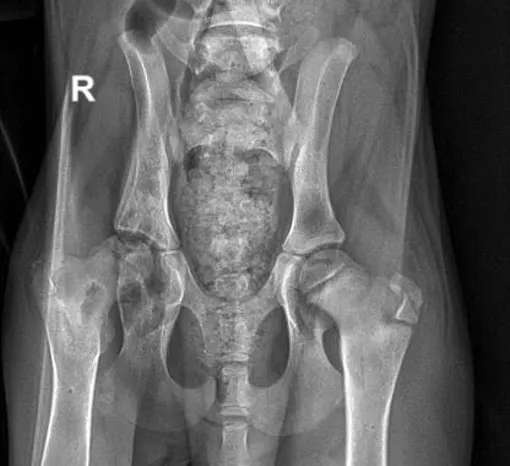
FIGURE 1 Radiographs of a 12-week-old German shorthaired pointer with a right septic coxofemoral joint infected with beta hemolytic Streptococcus spp. Bone production on the acetabulum and lytic lesions on the acetabulum, neck of the femur, and femoral head can be noted.
Diagnostics & Diagnostic Findings
An Ortolani test may be performed and may require sedation or anesthesia (Figure 2).
A positive Ortolani sign is any indication that the joint can be luxated or subluxated during the test. The examiner places pressure, forcing the femur dorsally while the dog is lying in lateral recumbency. The limb is slowly abducted while the examiner continues to place pressure from the distal femur toward the hip joint. Reduction of the femoral head into the acetabulum occurs when the limb is abducted if hip joint laxity is present.
A positive Barlow sign is present when dorsal force is placed on the femur by the examiner and the head luxates on adduction of the neck (first part of the Ortolani test).
A negative Ortolani sign does not indicate lack of joint laxity; radiography is indicated if signs of discomfort are present with hip extension. In mature dogs, hip dysplasia should be suspected in patients with pain and crepitus in the hips; radiographic signs can confirm OA.2
Biomarkers for hip dysplasia
Research is ongoing on serum and urine proteins as early indicators of hip dysplasia in dogs.
Urine proteins decreased in adult dysplastic dogs: crosslinked C-telopeptide of collagen type II and tissue inhibitor of metalloproteinase 1.37
Serum proteins decreased in adult dysplastic dogs: collagen type II cleavage, procollagen type II propeptide.37
Adult dogs with hip dysplasia have decreased hyaluronic acid in serum and increased serum procollagen type II C-propeptide and matrix metalloproteinase-9.35
Serum procollagen type II C-propeptide may indicate OA prior to radiographic signs of OA in dogs and humans.52,53
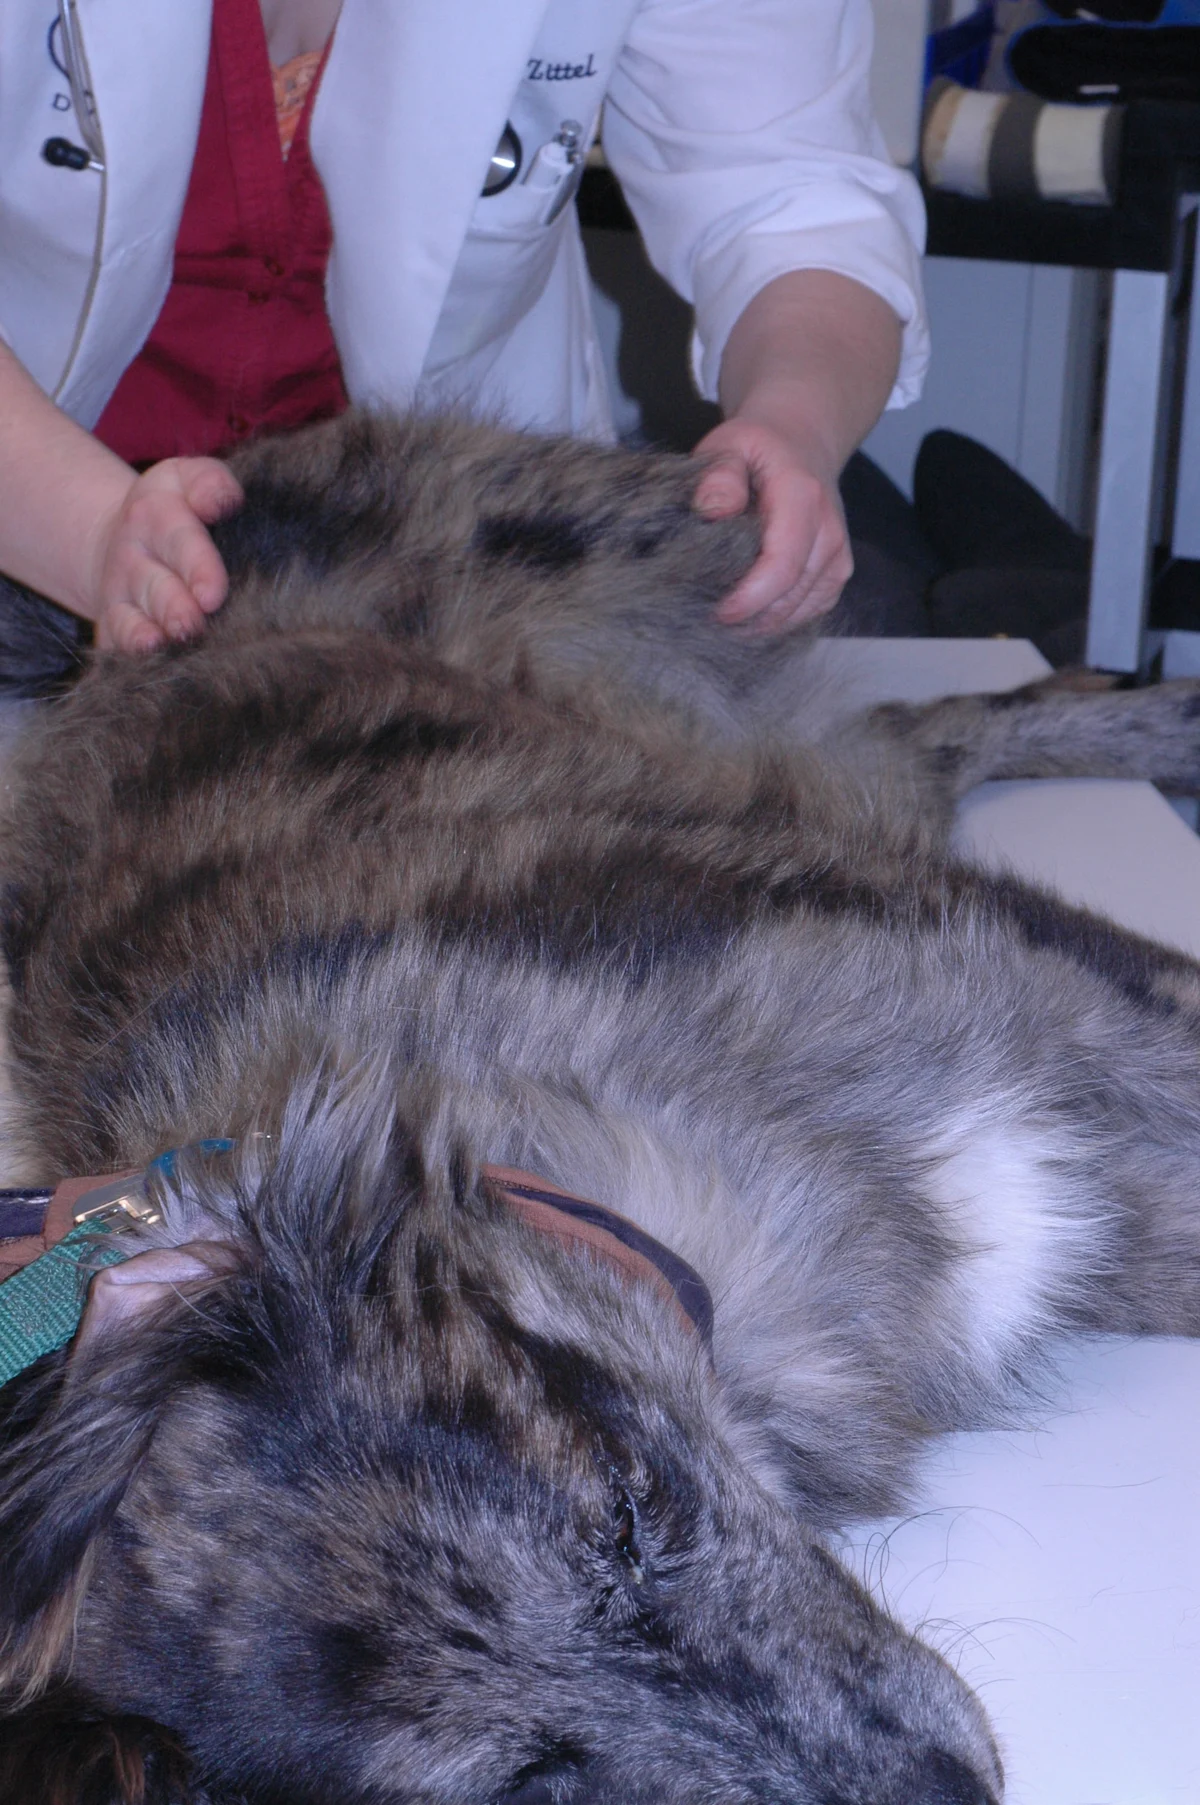
FIGURE 2 Proper positioning for Ortolani sign determination on physical examination of a dog is as follows. The dog is sedated and in lateral recumbency. The distal femur/stifle should be grasped and force placed on the femur dorsally toward the hip while the examiner’s other hand is on the dorsal aspect of the pelvis and lumbosacral spine (to stabilize the dog). In dogs with hip dysplasia, the hip is luxated or subluxated with this dorsal force (mimicking weight-bearing). While the examiner continues to place force on the distal femur dorsally toward the hip joint, the femur is slowly abducted until the coxofemoral joint is reduced.
Definitive Diagnosis
Several scoring systems for hip laxity and risk for development of hip dysplasia based on radiographs are available.
The Federation Cynologique Internationale (FCI) system used in Europe, Asia, and Latin America is a qualitative scoring system (ie, grade A-E) that assesses hip extension on ventrodorsal radiographs based on Norberg angles, angle of reduction, angle of subluxation, laxity index, and dorsal acetabular rim slope.
Grade A does not show radiographic signs of disease (ie, nondysplastic), and grades B (near normal) to E (severe) indicate presence of disease in varying severity.
FCI scores have identified breed-specific differences; however, significant differences between grade A and B radiographs were found in dogs <28 weeks of age, potentially offering another method of early detection of hip dysplasia besides the University of Pennsylvania hip improvement program (PennHIP) distraction index (DI), which is used to detect hip dysplasia in puppies ≥16 weeks of age.
The British Veterinary Association/Kennel Club system in the United Kingdom, Australia, and New Zealand is a qualitative scoring system that evaluates hip extension on ventrodorsal radiographs. This system has not been assessed in young dogs, unlike the FCI system and PennHIP DI.
The Orthopedic Foundation for Animals (OFA) in the United States uses a qualitative scoring system that evaluates ventrodorsal hip extension on radiographs in patients ≈2 years of age.
OFA integrates a voluntary database of dogs with certification for certain genetic clearances for the purpose of conformation showing, athletic competition, and breeding (see Orthopedic Foundation for Animals Certification).
Hip-extended ventrodorsal radiographs have a high rate of false-negative interpretations due to tightening of the joint capsule that causes the femoral head to move into the acetabulum. This system is not used for early diagnosis of hip dysplasia in puppies or dogs <24 months of age and may not be as sensitive as the PennHIP DI or FCI system.
Norberg angle measured on ventrodorsal hip extension radiography is also used to detect hip laxity.54-56
This angle is formed by connecting a point at the center of the femoral head (ball of the hip) to the upper acetabular rim hip socket.
Norberg angles >105 degrees are considered normal; however, angles consistent with hip dysplasia can vary by breed.
No radiographic technique can completely eliminate false-positive and false-negative findings when diagnosing hip dysplasia before onset of OA.54
Orthopedic Foundation for Animals Certification
To meet OFA review and certification for radiographic evaluation, the following criteria must be met:
Comprehensive examination performed on dogs 2 years of age
Microchip identification completed
Preanesthetic blood work conducted before radiographic evaluation
Preventive vaccinations and heartworm disease screening ensured to be up to date
PennHIP DI determines joint laxity in patients <1 year of age (Figure 3; see University of Pennsylvania Hip Improvement Program Fast Facts).
PennHIP DI can correlate with development of hip dysplasia later in life in dogs as young as 16 weeks of age but requires certification and a specialized apparatus to perform.
PennHIP DI has a low incidence of false-negative diagnosis for hip dysplasia, whereas OFA certification has a higher incidence.10,11 DI >0.3 generally indicates susceptibility to OA development, but some breed differences exist.
University of Pennsylvania Hip Improvement Program Fast Facts
Multifaceted radiographic screening method for hip evaluation
Can be performed on puppies as young as 16 weeks of age
Onset of hip OA related to hip dysplasia can be delayed by maintaining patients at risk for hip disease at a lean weight throughout their lifetime.
Valuable indicator of future hip OA
DI does not change significantly over time.
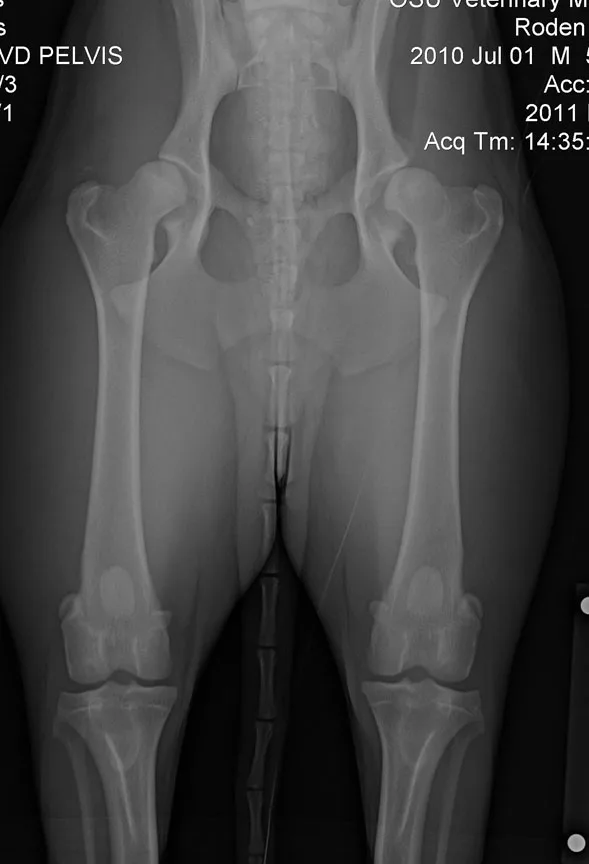
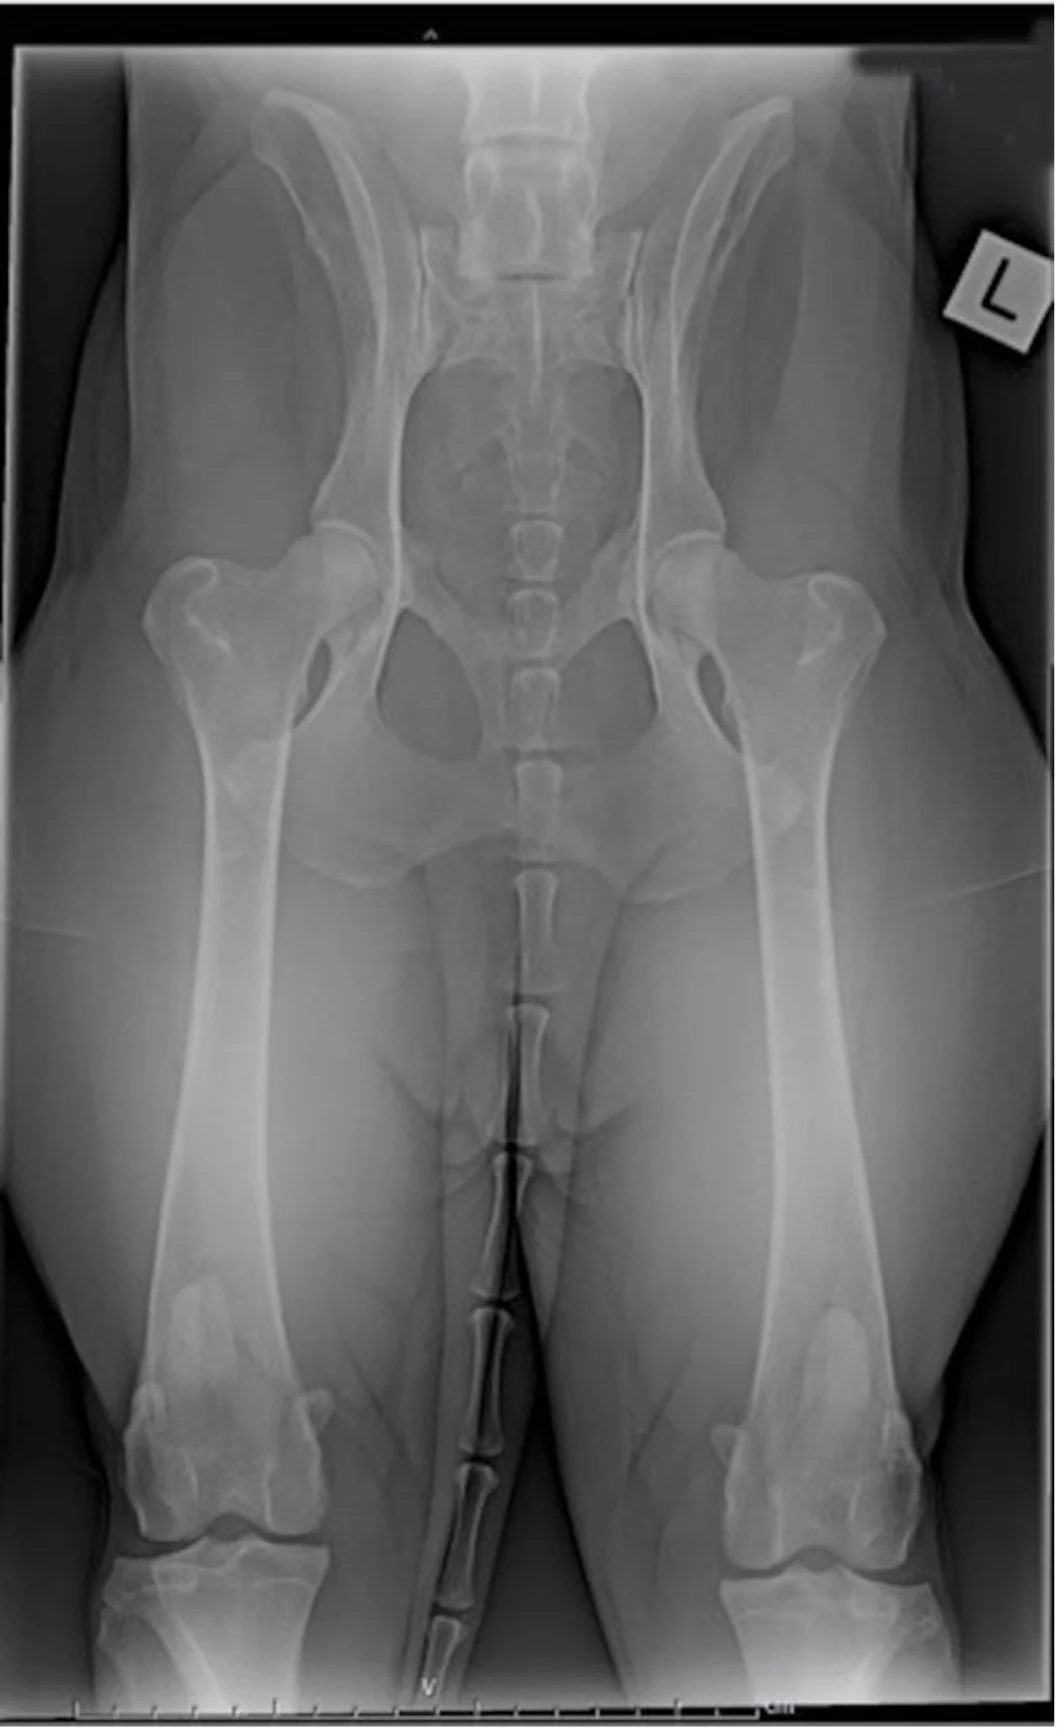
FIGURE 3 Hip-extended ventrodorsal radiograph of a 10-month-old Australian shepherd with lameness and bunny-hopping gait when running (left). Bilaterally decreased coverage of the femoral heads by the acetabula and laxity in the coxofemoral joints, with increased severity in the left joint, is present. Laxity can be seen in the left hip more easily as lateral displacement of the femoral head from the acetabulum. This can be compared with the nondysplastic adult hip radiographs (right), in which the joint space is narrow and uniform.