Blood Transfusion in Dogs
Julie M. Walker, DVM, DACVECC, University of Wisconsin-Madison
The author and Clinician’s Brief editorial team acknowledge the prior contribution of Nuno Manuel Félix, DVM, MD, MS, PhD.
Blood transfusion can provide life-saving treatment for patients with severe anemia and other disorders, but blood transfusions are not benign procedures. Adverse reactions occur in ≈7% of canine transfusion events.1 Safe administration of blood products requires precautionary measures, including careful sourcing of blood products; pre-transfusion testing in the recipient; and adoption of appropriate blood collection, processing, storage, and administration techniques. In the event of a possible transfusion reaction, several corrective measures should be followed and the cause identified.
This 3-part series covers blood collection and storage, patient selection, as well as administration and providing treatment for potential acute transfusion reactions.
Part I: Collection & Storage
Blood Product Sourcing
Blood products are available from animal blood banks and can be obtained in-house or from community-owned blood donors.2 Approximately 15 to 20 mL/kg of blood can be safely collected from a dog, although each donor should be monitored for signs of hypovolemia during and after blood collection.3,4 Administration of crystalloid solutions are not usually needed during blood collection from dogs. Blood products may also be acquired from patients with cavitary hemorrhage via cell salvage and autotransfusion techniques.5
Sedation is rarely needed during blood collection from canine donors. In cases in which sedation is elected, butorphanol (0.1-0.2 mg/kg IM or IV) with or without a benzodiazepine (eg, midazolam, 0.1-0.2 mg/kg IM or IV) commonly provides enough sedation and should be administered in conjunction with fear-free practices to reduce donor anxiety. Trazodone (2-5 mg/kg PO once 1-2 hours prior to travel for blood donation) can also be considered to reduce stress associated with transportation and arrival. If a significant amount of sedation is required, enrollment as a blood donor should be reconsidered, as anxiety related to donation might indicate lack of a positive experience for the donor.
Blood Donation Criteria
Canine blood donors must meet several conditions:
Clinically healthy and assessed with annual examinations and testing (see Donor Testing)
1-8 years of age
≥55 lb (22.7 kg)
Based on collection of ≈22% blood volume (BV) (≈20 mL/kg), a dog weighing ≥55 lb (22.7 kg) can donate 450 mL of blood. Commercially available blood collection systems for use in human blood donors are calibrated for collection of 450 or 500 mL (± 10%). Alternatively, donors should weigh at least 29.1 lb (13.2 kg) if a 250 mL collection system is used.
Normal body condition (preferably, BCS 4-6 [9-point scale])
Good temperament
Up-to-date vaccination status
Packed cell volume (PCV) ≥40%
Blood type negative or positive for dog erythrocyte antigen-1 (DEA 1) if performing DEA 1 type-specific transfusions.
DEA 1 type-specific transfusion of RBC products should be considered to optimize use of available blood resources.
Although a true universal canine donor lacking all red cell surface antigens does not exist, the ideal canine blood donor is negative for DEA 1, DEA 3, DEA 5, and DEA 7 and positive for DEA 4.6
Readily accessible jugular vein
No previous history of receiving blood product transfusions
Not presently pregnant or lactating
Pregnancy is not known to lead to alloantibody formation against erythrocyte antigens.7 Although a low percentage of dogs possessed anti-DEA 7 antibodies in a relevant study, there was no statistical significance in the prevalence of antibodies between dogs with (11.4%) and without (13.3%) a history of prior pregnancy.7 Dogs with a history of pregnancy should thus not be excluded from the donor pool.8 Dogs that are pregnant or lactating should be temporarily deferred for blood donation due to alterations in maternal physiology and fluid balance, as well as concern for fetal health.
Donor Testing
Knowledge of the donor blood type is critical. DEA 1 typing should be performed at a minimum, with additional testing to ideally include DEA 3, 4, 5, and 7. Blood donors should be thoroughly assessed to determine whether they are in excellent health. Health screenings should include:
CBC
Serum chemistry profile
Fecal analysis (every 6 months)
Infectious disease testing should be based partly on local and regional prevalence of infectious agents; however, national and international societies also have guidelines. The 2016 ACVIM Consensus Statement on Infectious Disease testing for blood donors recommends that canine blood donors test negative on the following infectious disease tests45:
Anaplasma spp (PCR ± serology)
Babesia spp (PCR ± serology)
Bartonella spp (PCR ± serology and/or specialized culture-PCR)
Brucella canis upon entry into program (or annually in breeding animals)
Ehrlichia spp (PCR ± serology)
Heartworm antigen
Hepatozoon canis americanum (geographic - PCR)
Leishmania spp (geographic and in foxhounds - PCR and serology)
Mycoplasma hemocanis (PCR)
Trypanosoma cruzi (geographic - serology)
Step-by-Step: Blood Donor Collection
What You Will Need
Cutaneous asepsis kit (ie, antiseptic solution, alcohol, gauze swabs, clippers)
Sterile gloves
Blood collection system (single or multi-bag system)
Gram scale
Plastic hemostat
Gauze and self-adhesive wrap
Metal clips or heat sealer
Step 1: Examine & Prepare the Blood Donor
Confirm the donor has been healthy without concern for current illness. Measure temperature, pulse, and respiratory rate. Place the donor in lateral recumbency. Evaluate the quality and location of the jugular vein. Shave and sterilize the skin around the jugular vein. Clip and aseptically prepare the skin at the blood collection site (at least 2 cm on each side of the planned needle insertion site).
Step 2: Prepare the Blood Collection Supplies
Wearing fresh examination gloves, place the collection bag on a gram scale and zero the scale. Avoid kinking or twisting in the tubing to prevent obstruction of flow or RBC damage. Clamp the collection line 3 to 4 cm away from the needle (use a plastic hemostat to avoid damage to the collection line), and remove the needle cap.
Author Insight
A multi-bag system should be used if blood components will be produced from the whole blood (WB) donation. Most commercially available blood collection systems include an anticoagulant-preservative solution (eg, citrate-phosphate-dextrose-adenine [CPDA-1], citrate-phosphate-dextrose) with or without a separate bag containing red cell additive solutions to extend the shelf life of packed RBCs (pRBC).
Step 3: Perform Phlebotomy
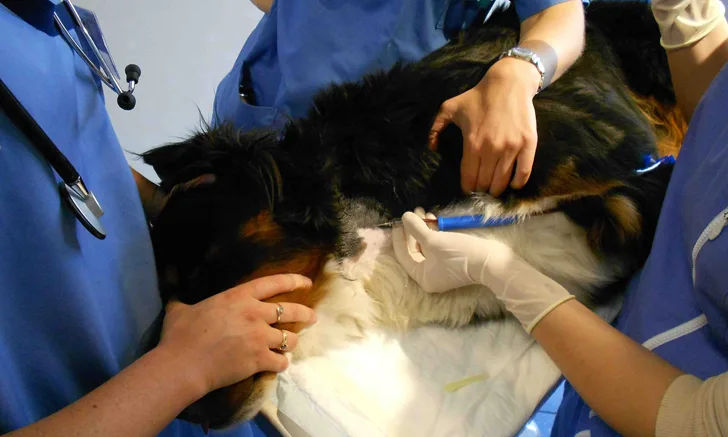
As an assistant compresses the thoracic inlet to increase jugular vein distension, insert the needle into the jugular vein in a cranial direction and with the bevel facing up without touching the insertion site. Once blood enters the collection system, remove the hemostat clamp, and let blood flow into the tubing and collection bag.

Photo courtesy of Dr. Isabelle Goy-Thollot, SIAMU/ICU, VetAgro Sup, University of Lyon
Author Insight
Diverting the first 10 mL of blood into a separate collateral bag is recommended to prevent contamination of the blood unit with skin microorganisms.9,10 This blood can be used for donor testing, if needed.
Step 4: Monitor the Blood Collection Process
During collection, the assistant carefully rocks the collection bag back and forth to allow blood to mix with the anticoagulant. Once 405 to 495 g of blood is collected, release the pressure to the thoracic inlet.

Photo courtesy of Dr. Isabelle Goy-Thollot, SIAMU/ICU, VetAgro Sup, University of Lyon
Clamp the collection line with an atraumatic plastic clamp, remove the needle, and perform compression over the puncture site for 1 minute. Wrap the jugular site with cohesive bandage wrap for at least 30 minutes to prevent bruising and hematoma formation.
Step 5: Seal & Label the Whole Blood Unit
Seal the collection line with metal clips or a heat sealer at least 3 cm above the bag to maintain a unique identifying line number on the bag. Create 3 to 4 pigtail segments that are ≈3 cm in length each and attached to the bag for pretransfusion compatibility testing. Label the collection bag with donor identification, as well as the date, time, and amount of blood collected.
Record details in the donor record, including body weight (BW), vital signs, and PCV/total solids before and 30 minutes after transfusion. Include data about vessel and draw position used, and record any problems that occurred.
Processing Blood Products
In the 4 to 6 hours after blood collection, blood can be administered as fresh whole blood (FWB), be refrigerated (39°F-42°F [4°C-6°C]) and stored as WB, or be refrigerated until processing for blood component therapy. Blood component therapy (commonly used in human and veterinary medicine) allows therapy to be tailored to the patient while avoiding transfusion-related reactions because the patient is spared exposure to unnecessary blood products. Blood component therapy allows for more efficient transfusion because a single unit can be divided into multiple components that can be used for more than 1 patient. Each blood component has unique indications, advantages, and disadvantages (Table 1).
Most blood components are produced by centrifugation using a large, temperature-controlled centrifuge. Specific settings (ie, speed, time, temperature of centrifugation) are recommended according the intended product being produced.
For example, to obtain pRBCs and fresh frozen plasma (FFP), WB is first centrifuged, then (with the use of a plasma extractor) the plasma supernatant is allowed to flow in to a satellite bag, leaving pRBCs in the primary collection bag (Figure 1). Addition of an additive solution to the pRBC unit should be clearly indicated on the blood product label along with the expiration date.
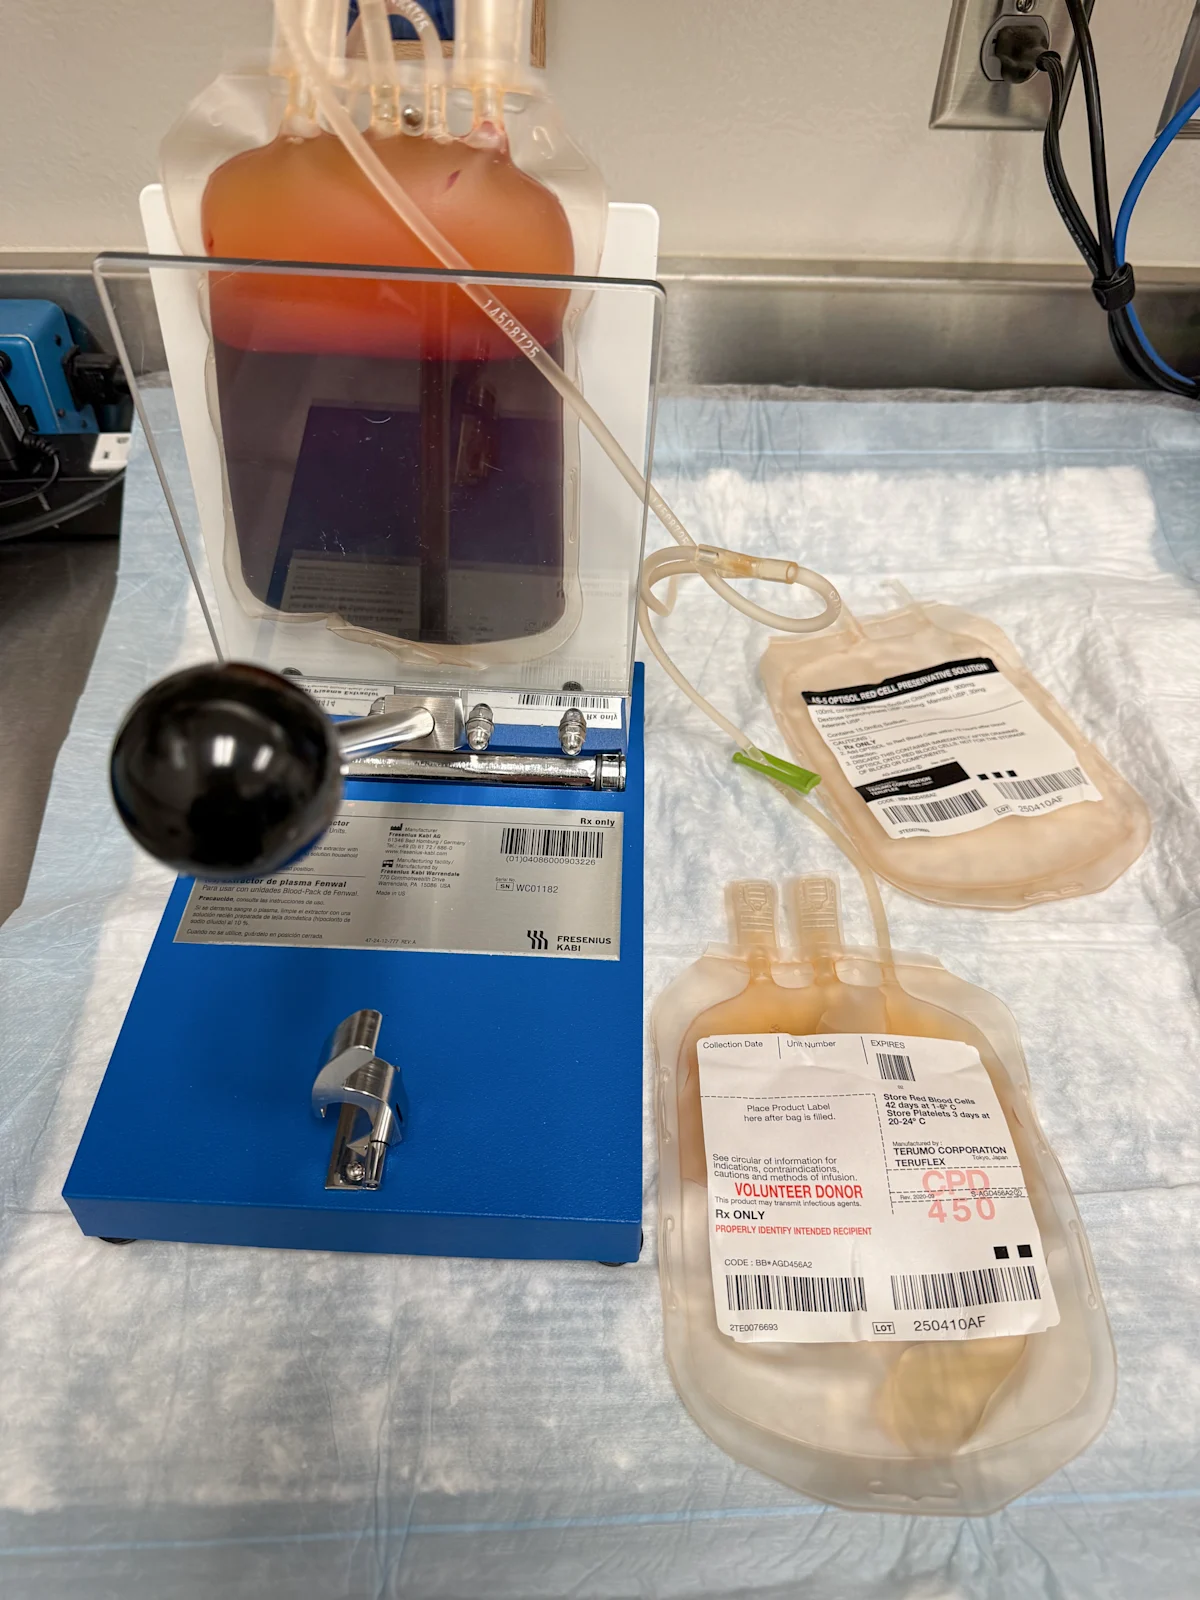
FIGURE 1 pRBCs and plasma separated through the aid of a plasma extractor. Photo courtesy of Emma Doubleday, CVT, University of Wisconsin-Madison
Examination gloves should be worn throughout while obtaining and handling blood products. Each product should be handled with care to prevent mechanical damage and contamination, ideally in a laminar flow chamber (Figure 2).

FIGURE 2 Blood products should be handled under the most aseptic conditions, ideally in a laminar flow chamber. Photo courtesy of Dr. Joana Gomes, Banco de Sangue Veterinário, Lisbon Faculty of Veterinary Medicine, Lisbon, Portugal
Pre-storage leukoreduction removes >99% of WBC ± platelets from WB or pRBC and is performed routinely in human blood banks. Leukoreduction filters have decreased the incidence of febrile nonhemolytic transfusion reactions and transmission of some infectious diseases in humans.11,12 Although not universal in veterinary medicine, some veterinary blood banks routinely use leukoreduction filters during production of canine blood components. Experimental evidence has shown that leukoreduction can reduce the posttransfusion inflammatory response in normal dogs,13 but evidence is mixed on whether leukoreduction practices reduce the incidence of transfusion reactions in clinical patients.1,14-16 As evidence accumulates, each veterinary blood bank should weigh the increased cost of production against the possible benefits to blood product recipients.
Storage lesions consist of changes in cellular (RBC, platelet) metabolism, protein activity and function, phenotype, and morphologic properties induced by storage. Over time, RBC units demonstrate an increase in reactive oxygen species, proinflammatory mediators, and microvesicle concentration, with the potential for adverse effects in the transfusion recipient.6,17
The Transfusions Reaction Small Animal Consensus Statement (TRACS) on the diagnosis, treatment, and prevention of transfusion reactions in small animals states that fresher RBC products should be considered in dogs with sepsis or hemolytic anemia.8,18,19 Two studies examining transfusion reaction rates in dogs have been published using the diagnostic criteria presented in this consensus statement. In the prospective multicenter study, pRBC storage >28 days was associated with a higher risk for hemolytic transfusion reactions compared to units stored <14 days.1 Whether hemolytic reactions were due to immunologic or nonimmunologic factors was not determined. Conversely, the retrospective study did not identify an association between pRBC age and occurrence of transfusion reactions.20
Test your knowledge of blood and transfusion products, from packed RBCs, whole blood, and fresh-frozen plasma, to blood typing and crossmatching in this quiz on Blood Transfusion Products in Dogs & Cats.
Blood Product Storage
Stored blood products should be labeled with donor species, blood product name, donor blood type, donor name, collection date, and expiration date. Maximum storage times for WB and blood components are listed in Table 2.
A dedicated refrigerator is critical for blood product storage. Temperature must be accurately measured and recorded throughout storage, and an audible alarm should sound when temperatures fall outside the target range. Absence of a dedicated refrigerator with continuous temperature monitoring has been linked to development of hemolysis in blood product units, leading to fatalities.21 A dedicated space may be acceptable in cases in which a dedicated refrigerator is not available, but blood products should be kept separate from other products to avoid chemical and biologic contamination.
Blood products should be stored vertically and with airspace between each bag but not in crisper drawers. Blood product storage refrigerators should be opened as infrequently as possible to prevent temperature fluctuations, which can cause damage to RBC products. Blood products with RBCs should be inspected and gently rotated every other day to allow mixture of RBCs with the anticoagulant.
If frozen blood products are stored in a residential-style freezer, the auto-defrost function should be disabled to avoid freeze–thaw cycling.
Autotransfusion of Blood in Patients with Hemorrhage
Blood obtained from closed cavities can be safely used for autotransfusion in conditions in which there is a low likelihood of intestinal, urinary, or biliary tract rupture or any other source of bacterial contamination. Other relative contraindications for autotransfusion are neoplastic disease and prolonged (>72 hour) dwell time in a body cavity.5 The chance of metastasis may be reduced with use of leukoreduction filters, with or without automated cell salvage devices.22,23
Blood removed from closed cavities for autotransfusion can be collected in a 60-mL syringe, empty sterile crystalloid fluid bags, or blood collection bags.5 A centesis collection kit comprised of a sterile 1 liter bag, tubing, and an integrated centesis valve is now available and is a convenient option for collection and administration of large volume cavitary hemorrhage (see Suggested Reading). Citrate-based anticoagulant (0.05-0.14 mL for each mL of collected blood) may be added to the syringe or bag; however, because blood becomes defibrinated when in contact with serosal surfaces for >1 hour,24 the amount of anticoagulant can be decreased if blood is present in body cavities longer than this period. Upon reinfusion, a blood filter must be used to prevent introduction of blood clots into circulation. The coagulation system status of the recipient should be carefully monitored after the transfusion, especially during the first 72 hours posttransfusion.
Part II: Patient Selection
Transfusion Decision-Making
The decision on whether to perform transfusion should be made based on the individual patient after evaluation of several components, including clinical signs (especially related to cardiovascular and respiratory systems), laboratory values (eg, hemoglobin, PCV, lactate levels), underlying disease, and the speed at which hemoglobin or RBC count decreases.25,26 A scoring system based on clinical signs (eg, mucous membrane color, pulse quality, heart rate, mentation, exercise intolerance) can help decide when to transfuse pRBCs to anemic dogs.26
RBC transfusions are usually administered to dogs when hemoglobin is <5.8 g/dL (58 g/L)or PCV is <17%.26 Because optimal transfusion triggers have not been determined for small animal species, human medicine guidelines can be used as a starting point.
In hemodynamically stable human patients, withholding transfusion until hemoglobin reaches <7 to 8 g/dL (ie, restrictive transfusion threshold) is recommended.27 Restrictive strategies can reduce patient exposure to RBC transfusion without affecting overall patient mortality, compared with a liberal hemoglobin threshold of 9 to 10 g/dL.27,28 In humans, some patients with critical neurologic disease and pre-existing cardiovascular disease may benefit from the higher transfusion threshold.27,28
For patients with acute hemorrhage, hemoglobin thresholds are unreliable and should not be used alone as triggers for transfusion. Multiple data points (eg, approximate blood loss, heart rate, blood pressure, pulse pressure, respiratory rate, urine output, Glasgow coma scale, base deficit) should be considered to determine the need for blood products.29
Confirming Blood Product Compatibility
Blood product and recipient compatibility is assessed by blood typing and crossmatching.
Blood Typing
Dogs have several blood types, with the majority belonging to the DEA system. The most commonly tested blood types include DEA 1, DEA 3, DEA 4, DEA 5, DEA 7, and Dal, although new blood groups (eg, Kai) continue to be identified.6,30,31 DEA 1 is the most clinically important of these blood groups, as it has the strongest antigenicity, is highly prevalent, and exists with nearly equal distribution of DEA 1-positive and DEA 1-negative dogs among breeds globally.32 DEA 1 was previously believed to consist of 3 subgroups (ie, DEA 1.1, DEA 1.2, DEA 1.3); however, these differences are now understood to be due to varying surface protein expression levels.33
Dogs do not have natural alloantibodies to DEA 1; if a DEA 1-negative dog receives DEA 1-positive blood, an initial antibody-mediated reaction will not occur; however, transfusion of donor cells that are weakly positive to a negative recipient will incite antibody production against the DEA 1 antigen,34 and a second exposure will likely induce a severe hemolytic reaction. Consequently, a DEA 1 blood type should be established for all blood recipients, and either DEA 1-negative or DEA 1 type-specific blood products should be administered to minimize the chance of sensitization.
Low-titer, naturally occurring antibodies are present in a minority of dogs negative for DEA 3, DEA 5 and DEA 7. Although evidence that these antibodies cause acute hemolytic transfusion is limited, delayed hemolysis is possible in recipients negative for DEA 3, DEA 5 and DEA 7 antigens.6,35 Most non-Dalmatian dogs are positive for the Dal antigen and, although naturally occurring anti-Dal antibodies are not known to exist, the antigen is strongly antigenic after transfusion-induced sensitization.31
Ideally, blood typing should be performed in the donor and recipient before every transfusion to prevent incompatibility reactions; however, blood typing in most clinics is restricted to determining DEA 1 status with in-house kits. Blood typing to other groups is available in a few specialized blood service laboratories. Blood group determination other than DEA 1 is predominantly used for donor screening or to evaluate crossmatch incompatibility.
A rapid immunochromatographic (IC) test and an agglutination card test are most commonly used to determine DEA 1 status. Results from these tests are generally comparable, although the former may be superior in dogs with immune-mediated hemolytic anemia, as results are not affected by agglutination. Although interpretation of all typing kits is subject to user error, the IC test can detect all levels of DEA 1 antigen expression (from very strong to very weak) while operators may miss mild agglutination using the card-based test.36
In cases in which the recipient blood type is unknown and blood typing is not available, only blood products from a DEA 1-negative donor should be used.
Crossmatching
A crossmatch test determines the serologic compatibility between the donor and recipient through an agglutination reaction. An incompatible crossmatch occurs when RBCs attach to naturally occurring preformed alloantibodies or antibodies produced in response to a previous exposure to RBC antigens. A major crossmatch involves the combination of donor RBCs against recipient plasma, looking for antibodies in the recipient that might react with transfused RBCs. A minor crossmatch combines recipient RBCs with donor plasma.
A major crossmatch should always be performed in patients with history of a previous transfusion reaction, unknown recipient transfusion history, and/or unknown donor DEA 1 status, as well as prior to a second transfusion if the first transfusion was >4 days earlier.18
A crossmatch can be performed by tube, gel-based, or IC methods37:
Tube crossmatch
RBC are washed several times, then diluted to a predetermined concentration (eg, 4%) in buffered saline.
Control: Donor RBCs are combined with buffered saline and donor plasma.
Test-reaction (major crossmatch): Donor RBCs are incubated with recipient plasma or serum.
Antiglobulin may or may not be added, depending on the protocol.
All tubes are incubated at body temperature.
Resultant reactions are examined macroscopically for hemolysis and agglutination, then for microscopic agglutination.37,38
Presence of hemolysis or agglutination indicates crossmatch incompatibility between the recipient and tested donor(s). Lack of these findings indicates a negative (compatible) crossmatch.
Protocols are tedious and not universally standardized, leading to variation in testing accuracy.38
Gel-based crossmatch (Figure 3)
Point-of-care test kits contain gel tubes and are available with standardized instructions. Depending on the manufacturer, the gel may be enhanced with antiglobulin.
Test reaction: Donor RBCs and recipient plasma are mixed, incubated, placed into the gel tube, and centrifuged. (Specific instructions may vary between manufacturers.)
Some test kits also come with positive and negative controls.
A compatible (negative) crossmatch occurs when all visible RBCs move to migrate to the bottom of the tube following centrifugation.
A positive (incompatible) crossmatch demonstrates that some or all of the RBCs remain suspended in the top or middle portion of the gel. Suspended cells represent agglutination, as RBCs bound to antibodies will not move as freely through the gel.
There is moderate agreement between the gel method and the standard laboratory tube method,37 and antiglobulin-enhanced gel methods might further improve test sensitivity and/or accuracy.
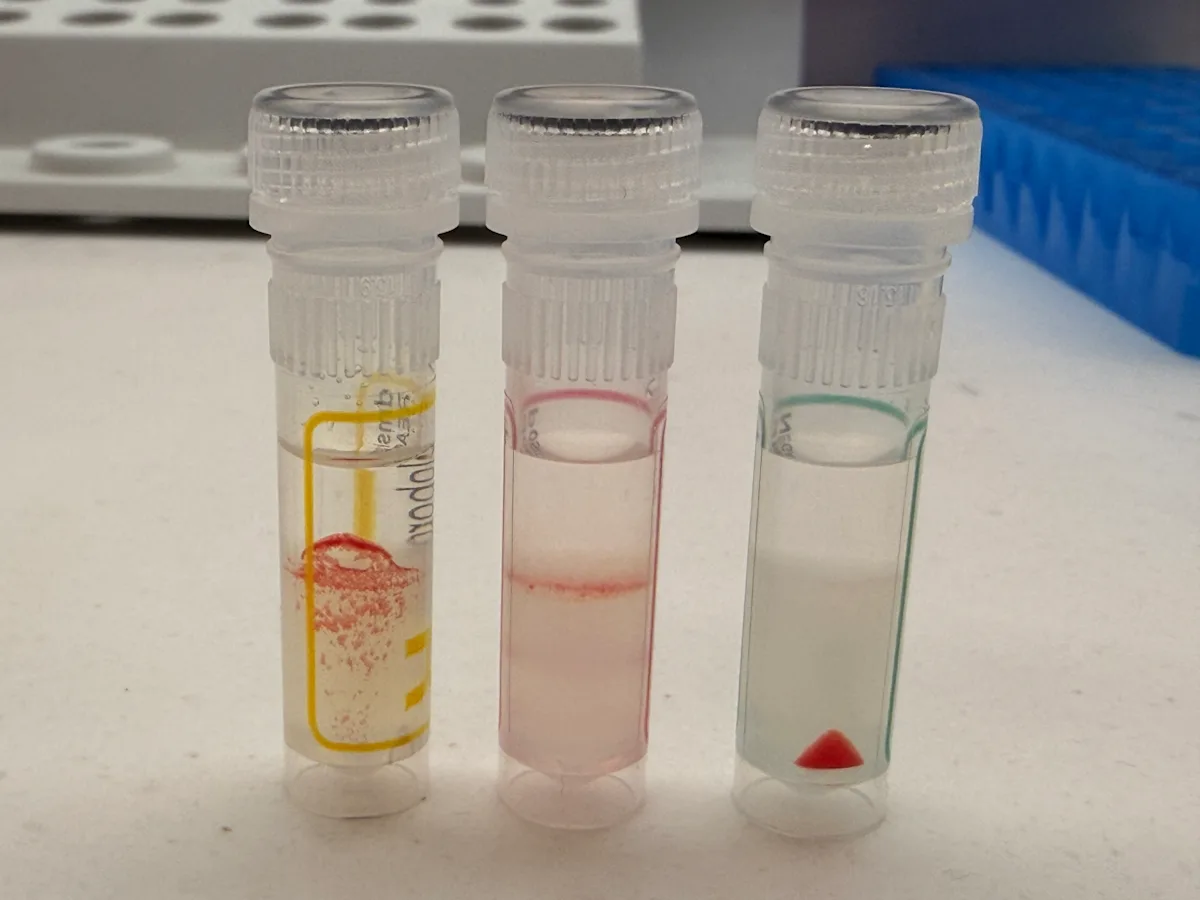
FIGURE 3 Results from a gel-based crossmatch test, including an incompatible sample (left), positive control (middle), and negative control (right). Photo courtesy ofVEG ER for Pets, White Plains, New York
IC strip crossmatch (Figure 4)
RBCs are combined with an included buffer solution and plasma.
After incubation, the sample is centrifuged, and the supernatant is discarded.
A second buffer solution is added and used to resuspend the RBC.
The test strip is placed into the tube, and the solution migrates along the strip. Antiglobulin is integrated into the test strip.
The RBC mixture usually migrates along the IC strip and produces interpretable results even in samples with RBC agglutination.
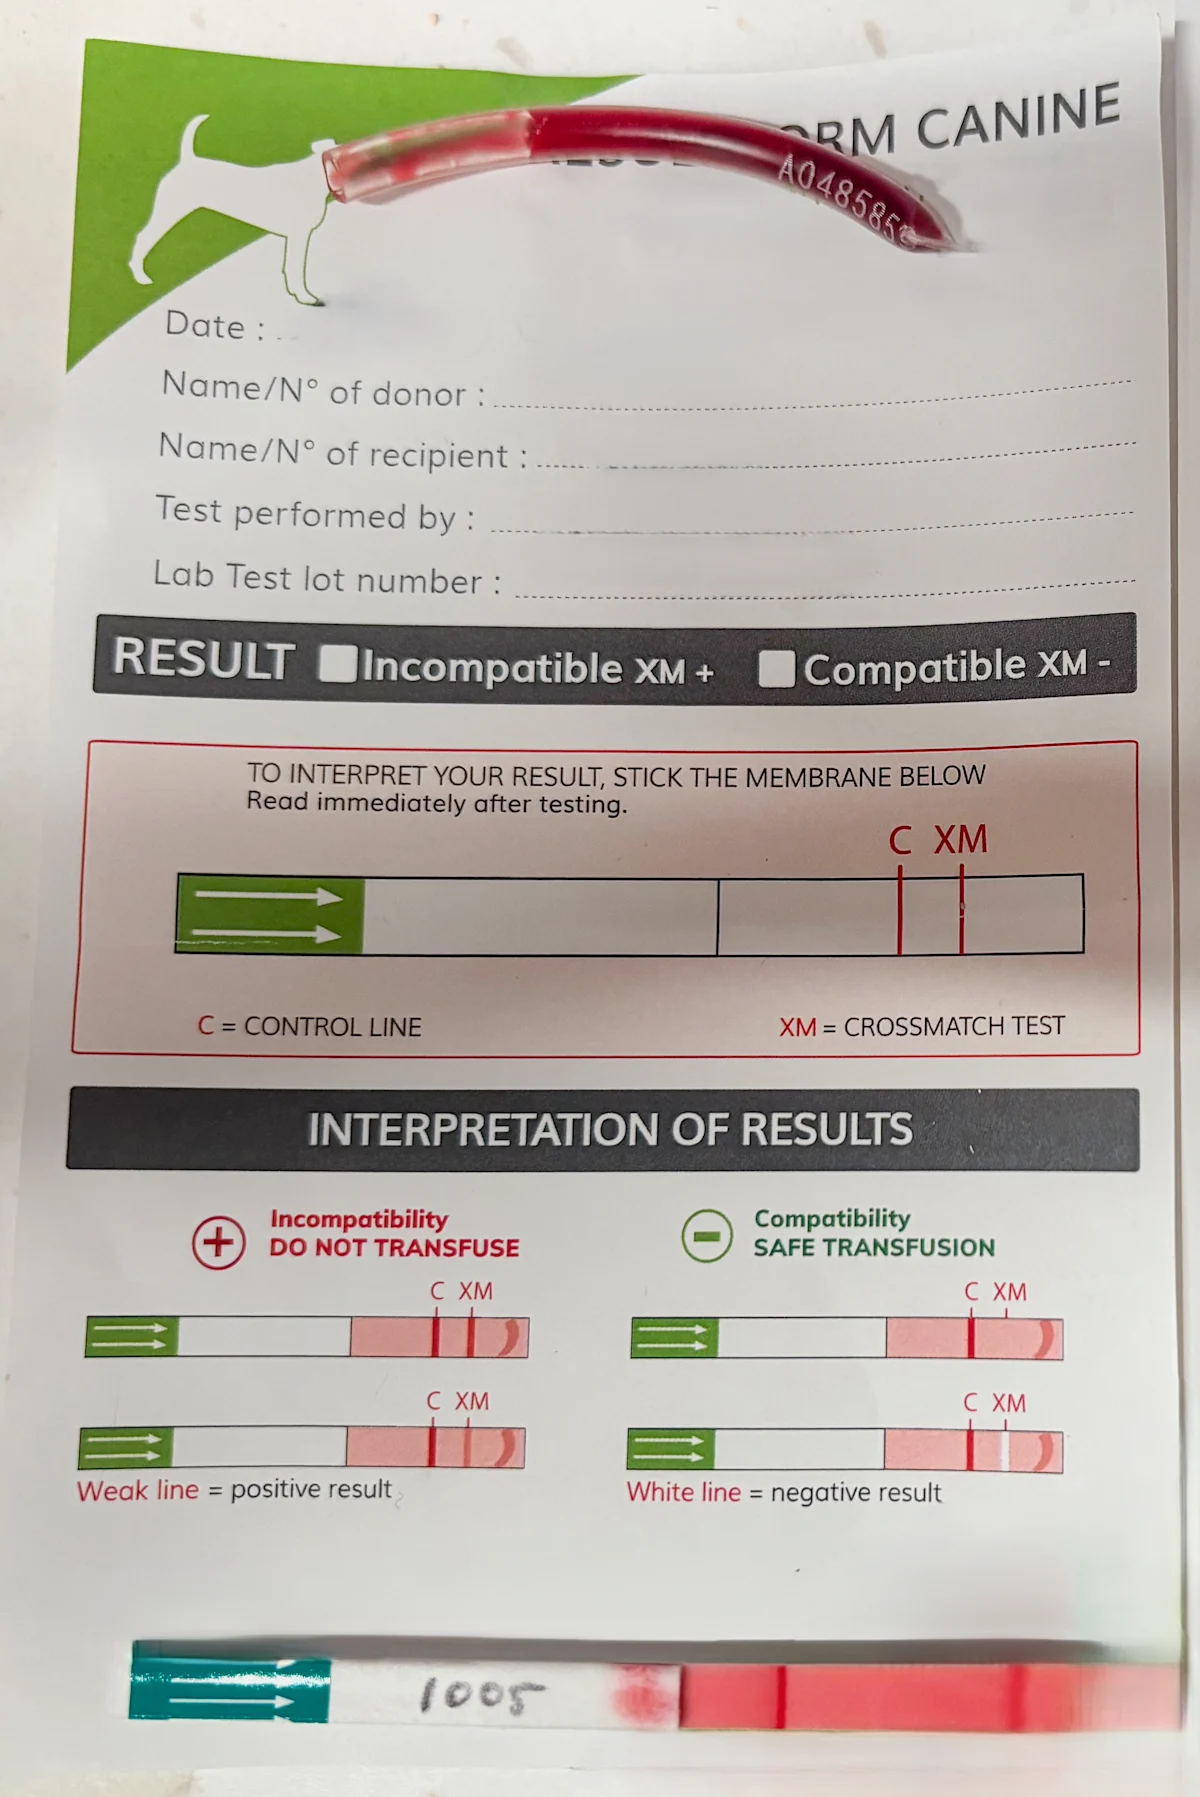
FIGURE 4 An IC strip crossmatch test showing a compatible result, with a results recording sheet. Each recording sheet contains example images to assist with test interpretation. Photo courtesy of Dr. Cory Romans, Veterinary Emergency Group, Madison, Wisconsin.
No single crossmatch method is ideal for all canine patients, as each method has strengths and weaknesses. Optimal results might be achieved when crossmatch tests are run with and without antiglobulin enhancement, although this is impractical for most clinical settings.39 Any of the crossmatch methods described above are considered reasonable options for critically ill canine patients.
Part III: Administration & Transfusion Reactions
Preparing to Administer Blood Products
Within reason, the blood product most appropriate to the patient’s condition should be chosen. This choice might be limited by product availability and urgency of the patient's need. For example, an unstable patient with severe anemia due to immune-mediated hemolytic anemia might ideally receive pRBCs because they contain less plasma; however, if a blood product centrifuge or banked products are not available, the most practical option is freshly collected WB from a prescreened donor, in which case the risks of transport-related delays must be weighed against the benefits of access to other products, in light of the patient’s stability.
When using WB or pRBC transfusion to increase oxygen-carrying capacity, a starting goal is to increase the PCV by 10% from baseline. The volume to be transfused can be determined with the following formulas.6,40 These formulas are only accurate if the patient does not experience significant ongoing blood loss or hemolysis.
For WB or pRBCs:
VT (mL) = BW (kg) × BV (90 mL/kg) × [(desired PCV−recipient PCV)/unit PCV]
For pRBCs with PCV ≈60%:
VT (mL) = 1.5 × desired rise in PCV × BW (kg)
pRBCs stored with an additive solution should not be administered with normal saline, as their PCV is ≈55% to 65%. In contrast, pRBCs not stored with a preservative solution have a PCV of ≈80%; consequently, the unit should be resuspended in normal saline. To promote an adequate transfusion rate, 10 mL of 0.9% sodium chloride is typically added per 30 to 40 mL of pRBCs.
Frozen blood products should be handled carefully during removal from the freezer because the edges of the bag are prone to breakage at near-freezing temperatures. Ideally, the bag should remain in a storage box and remain at room temperature for 10 to 15 minutes to allow the plastic to soften before handling. Frozen products can be thawed to 86°F to 98°F (30°C to 37°C) with a warm water bath and protected from water with a waterproof bag.
Pre-emptive use of corticosteroids has not been shown to prevent transfusion reactions and should not be used.41 According to TRACS recommendations, prophylactic use of antihistamines in patients with or without a prior history of allergic reactions is not recommended due to insufficient supporting evidence in humans.18 In addition, pretreatment with antipyretics is not suggested for prevention of febrile nonhemolytic transfusion reactions in dogs.18
Step-by-Step: Administration of Blood Products
What You Will Need
Gloves
Peripheral venous catheter (ideally, >22 gauge)
For large volume transfusions >100 mL:
Blood administration set with incorporated macroaggregate filter (pore size, 150-270 μm)
For transfusions up to 100 mL:
Injection spike (for use with large-bore (18- or 20-gauge) needles or a needle-free connector)
60-mL syringe
Inline macroaggregate filter
Microbore extension line
0.9% sodium chloride for IV infusion
Transfusion monitoring record
Step 1: Inspect the Blood Product
Before administering the blood product, verify that the species, blood type, and donor information (considering compatibility testing results) are correct on the product label and the product is not expired. Inspect the blood product for evidence of leakage or discoloration (RBCs typically settle toward the bottom of the bag, leaving a plasma line before pRBC units are disturbed). Observe the plasma color for evidence of moderate to severe hemolysis.
Author Insight
Units with bacterial contamination may contain blood clots or excess air bubbles or exhibit a dark purple to black color due to bacterial oxygen consumption.42 Units with such changes in appearance should not be used for transfusion. Units should also not be administered if there is any concern for leakage, as bacterial contamination is likely.
Step 2: Prepare the Blood Product/Administration Setup
Administer blood products IV (or via intraosseous catheter). Wear gloves, and use an aseptic technique. For transfusions >100 mL, use transfusion specific IV lines equipped with inline macroaggregate filters to spike the blood unit directly. For transfusions up to 100 mL, use an injection spike, large bore needle (if applicable), and 60-mL syringe to pull up the desired volume.
Author Insight
Blood products with RBCs should only be delivered via syringe or volumetric pump (if the equipment has been validated for this purpose). Peristaltic and rotary infusion pumps should generally be avoided in favor of gravity flow or piston pumps, and macroaggregate filters (150-270 μm) should be used for administration of RBC products in dogs.18,43 Microaggregate filters (18 μm) can be used for administration of plasma products, according to manufacturer instructions.
Step 3: Deliver the Transfusion
Initiate the blood transfusion (eg, 0.25 mL/kg/hour) for 15 minutes. If no evidence of a transfusion reaction (eg, unchanged vital signs and no new hypotension, vomiting, dyspnea, urticaria) is noted after 15 minutes, increase the rate to the full administration rate thereafter.18
Author Insight
Blood products exposed to room temperature conditions should be administered within ≤4 hours to minimize bacterial growth.43 For patients expected to be at risk for volume overload, the transfusion can be divided into aliquots, and each aliquot should be administered over ≤4 hours. Any blood product that has been punctured (eg, an open system has been created when spiked with a fluid set or injection port) should be refrigerated when not in use and discarded within 24 hours of initial entry.
Blood products can be administered rapidly (eg, 10-20 mL/kg over 30-60 minutes) in patients with massive hemorrhage or concern for imminent death from anemia. Slower administration (eg, over 2-4 hours or longer if units are divided into aliquots) should be used in more stable patients.
Step 4: Monitor the Transfusion Recipient
Record patient and administered blood product information on a transfusion monitoring record (eg, transfusion monitoring sheet provided in the TRACS guidelines).18 Immediately prior to transfusion, record the recipient’s temperature, pulse/heart rate, mucous membrane color, capillary refill time, respiratory rate and effort, mentation, and blood pressure. Monitor these parameters every 15 minutes for the first hour, then every 30 to 60 minutes until one hour after transfusion is complete, then continue monitoring vital signs every 4 to 8 hours for the first 24 hours after transfusion. Use sterile 0.9% sodium chloride to flush the remainder of the blood product into the patient’s catheter.
Evaluate and record PCV/total solids and plasma color before and after transfusion; repeat if any complications arise. Record any adverse reactions, including but not limited to urticaria, facial swelling, vomiting, and nystagmus, and pause the transfusion if any of these signs are noted until additional investigation is complete.
Author Insight
The TRACS guidelines provide recommendations for evaluation and next steps in patients with suspected transfusion reactions.19 Blood transfusion monitoring should continue during the first 24 hours following the transfusion (although less frequently) because some adverse reactions to blood transfusion can be delayed.
Blood filters should be replaced after filtering a maximum amount of blood as specified by the manufacturer. For example, if an 18-μm filter is used, the filter should be replaced after every 50 mL of transfused blood to prevent system obstruction. If multiple transfusions are administered through a blood filter, the filter and administration set should be discarded every 4 hours, or sooner if any suspected complications occur.44
Identification & Management of Transfusion Reactions
Transfusion recipients should be monitored closely. If an acute transfusion reaction is suspected, the transfusion should be stopped immediately until further information is gathered. The volume of infused product and the infusion rate should be recorded. The patient should be examined, with prioritization of vital signs and evaluation of the airway, breathing, circulation, and neurologic status. The unit’s expiration date should be rechecked, and its visual appearance should be reinspected for discoloration or evidence of particulate matter. A blood sample should be collected from the recipient to assess plasma hemolysis (eg, in a centrifuged capillary tube), and any pigmenturia should be noted).
Based on evaluation of the patient, the algorithms presented in the TRACS guidelines can provide information on whether the unit can still be administered or should be discontinued.19 Even if the product must be discontinued, the blood product and administration set should be reserved for further evaluation (eg, culture, evaluation for unit hemolysis, crossmatch testing).
Transfusion reactions may be acute (during or immediately following transfusion) or delayed (days to weeks later), immunologic (involving an interaction between immune proteins and cells between the donor and recipient) or nonimmunologic (related to chemical factors, physical damage to transfused RBC, or transmission of infectious organisms), and vary in severity. TRACS guidelines provide diagnostic criteria and recommendations for monitoring and treatment of transfusion reactions, including treatment algorithms for patients demonstrating respiratory distress, fever, tachycardia/hypotension, or vomiting during or immediately following blood product transfusions.18,19
Febrile Transfusion Reactions
A new-onset fever that occurs during or within 4 hours following a transfusion might signal a febrile nonhemolytic transfusion reaction (FNHTR), acute hemolytic transfusion reaction (AHTR), transfusion-transmitted infection, or other underlying condition.
Febrile Nonhemolytic Transfusion Reaction
FNHTR is the most common transfusion reaction in dogs undergoing RBC transfusions and is most likely in patients with no evidence of hemolysis, respiratory changes, or cardiovascular instability.1 Signs secondary to FNHTR are usually mild and self-limiting, in which case transfusion can usually be restarted at the same or a lower rate after the patient is stable without evidence of new hemolysis.19
Acute Hemolytic Transfusion Reaction
Signs of an AHTR may include fever, increased respiratory rate and effort, generalized discomfort, epistaxis, or hypotension. Patients that develop AHTRs are at increased risk for circulatory shock, respiratory distress, disseminated intravascular coagulation, or secondary organ injury. The transfusion should not be restarted in patients with evidence of AHTR.19 Supportive care (eg, IV fluid therapy, oxygen, vasopressors) should be provided as needed. Following stabilization, an underlying cause of the AHTR should be investigated. Recipient blood type and donor cells should be confirmed, and retrospective crossmatching using a sample of the administered RBC product and a recipient blood sample collected prior to transfusion should be considered.
Bacterial Infection
Septic transfusion reaction is a type of transfusion-transmitted infection that occurs secondary to administration of blood products contaminated by pathogens, most commonly bacteria. In addition to fever, patients may demonstrate tachycardia, hypotension, and other signs (eg, respiratory distress, GI signs). If these signs develop acutely during transfusion, Gram staining and microscopic inspection of the blood product should be performed. If RBC contamination is suspected, an anaerobic and aerobic culture of the blood product and the patient’s blood should be performed, and empirical broad-spectrum antibiotic therapy should be provided until culture and susceptibility results are available.19
Allergic Transfusion Reactions
The second most common type of transfusion reaction in dogs is the acute allergic transfusion reaction, occurring more commonly in plasma product recipients.1 Allergic reactions are typically mild and limited to cutaneous signs (eg, erythema, urticaria, angioedema, pruritus), although anaphylactic reactions (eg, hypotension, tachycardia, bronchoconstriction, GI signs) can occur. Antihistamines are recommended for management of cutaneous signs in patients with allergic transfusion reactions.19 If stable patients with mild allergic reactions limited to cutaneous signs demonstrate improvement after antihistamine administration, the transfusion may be resumed under close observation44; however, the transfusion should be discontinued in patients with moderate allergic reactions or anaphylaxis.
Epinephrine should be administered as part of first-line therapy in patients with cardiovascular or respiratory instability secondary to anaphylaxis.19,44 Other supportive care (eg, IV fluids, oxygen, antiemetics) should be considered. TRACS guidelines suggest that glucocorticoids should be avoided due to concern for adverse effects.19
Respiratory Transfusion Reactions
Tachypnea and/or increased respiratory effort developed during or within 6 hours after a transfusion warrants close patient evaluation. Abnormal respiratory rate or effort may be caused by transfusion-associated circulatory overload (TACO), transfusion-related acute lung injury (TRALI), a secondary sign of AHTR, or a comorbid condition (eg, aspiration pneumonia). Patients with respiratory reactions that occur in association with transfusion and in which these other causes have been ruled out are deemed to have transfusion-associated dyspnea.19
For all respiratory transfusion reactions, supportive care (eg, oxygen supplementation, treatment for anxiety related to dyspnea) throughout the patient assessment is recommended. A single dose of furosemide should be considered, particularly if the patient is not initially stable enough to undergo diagnostic testing.
Transfusion-Associated Circulatory Overload
Thoracic radiography, echocardiography, NT-proBNP measurement, and response to a single “trial dose”of furosemide may provide insight into the likelihood of TACO. If TACO is suspected, the patient should be managed with conservative doses of furosemide (eg, a single dose of 1-2 mg/kg IV usually leads to improvement in clinical signs) and supportive care measures provided in cases of volume overload. Additional blood product administration may be considered after signs of TACO have improved, using caution to administer products slowly (possibly in aliquots) and under close observation. Patients with TACO often require less aggressive doses of furosemide compared with patients with naturally occurring congestive heart failure.19
Transfusion-Related Acute Lung Injury & Transfusion-Associated Dyspnea
Therapy for TRALI and transfusion-associated dyspnea is focused on supportive care (eg, IV fluids, oxygen supplementation via nasal cannula, oxygen cage, high-flow nasal oxygen, or via mechanical ventilation). Beyond an initial trial dose (eg, to determine the likelihood of TACO), ongoing furosemide is not indicated because pulmonary dysfunction with TRALI occurs secondary to pulmonary inflammation rather than via increased hydrostatic pressure.19
Other Transfusion Reactions
Vomiting can occur as part of hemolytic, febrile, septic, or allergic transfusion reactions and be part of an unclassified transfusion reaction or related to an underlying condition. Full examination for signs of instability or evidence of a severe transfusion reaction should be performed in any patient that vomits during or immediately after a blood transfusion. Transfusion following antiemetic therapy can be restarted in patient’s deemed stable with no other reaction.19
Citrate, the main anticoagulant in blood products, prevents coagulation through the chelation of calcium. Hepatic metabolism of citrate is usually sufficient in patients receiving single transfusions; however, hypocalcemia and associated signs (eg, facial paresthesia/rubbing or swelling, tremors, seizures, hypotension, QT prolongation, nausea) can occur in patients receiving large transfusion volumes in a short period. Calcium supplementation is recommended in transfusion recipients with ionized calcium ≤0.9 mmol/L (reference interval, 1.16-1.40 mmol/L). In addition, calcium supplementation can be considered in patients receiving massive transfusions (eg, half of the patient’s BV administered over 3 hours, full BV administered in 24 hours).19
Conclusion
Blood transfusion can be a life-saving therapy, but there are risks. Careful donor screening, recipient pretransfusion testing, and blood product selection can help reduce transfusion risks. Close recipient monitoring and knowledge of transfusion reaction pathophysiology and management are essential for maximizing benefits and minimizing complications. A systematic approach can help deliver safe, effective care in routine and emergency settings.